


A couple of weeks ago, I used the publication in The New York Times of an article describing how the journalist’s father had become ensnared by Envita, an “integrative oncology” clinic after he had been diagnosed with lung cancer, how the clinic milked him for all the cash it could, and how her father had died in a nearby ICU, far from home, friends, and most family, to discuss a more general phenomenon of these quack clinics and how they prey on desperate cancer patients. Although I’ve long thought about how these clinics advertise seemingly miraculous results—”cures,” even—on social media to lure patients with advanced cancers for which conventional science-based oncology can offer only palliative care, my anecdotal personal experience writing about this phenomenon doesn’t necessarily reflect reality, other than my perception of these clinics as profiting on quackery and misery. So it was that I became aware of a couple of recent studies, one from Taiwan and one from France, that examine the phenomenon from the perspective of who chooses these clinics.
The Taiwanese study looks at why women with breast cancer choose traditional Chinese medicine to treat their disease, while the French study is more general and asks why people. Both studies, as you will see, suffer from the problem of not being willing to label correctly the aspects of integrative oncology that are quackery, as well as from a bias towards academic integrative medical centers, which tend not to go nearly as far recommending unproven therapies and to use “integrative” approaches only for symptom management, not to treat the cancer (although that is not always the case, given some examples of rank quackery I’ve found over the years at university-affiliated academic integrative oncology programs). Perhaps the greatest weakness is that neither considers many of the freestanding “integrative oncology” clinics and medical centers that are not only not constrained by evidence, but also unconstrained by affiliation with a university or academic medical center with a reputation to maintain. I was reminded by that of a post at ETP News examining what happened when an investigator actually went undercover posing as a patient with stage IV colon cancer to seek “integrative” oncology care.
Integrative oncology in France
I’ll start with the French study first. Entitled Integrative oncology consultation and patient referral to complementary therapies: results from the prospective study THERAC and published in the journal Supportive Care in Cancer, it comes from investigators at the Département Interdisciplinaire des Soins de Support en Oncologie (Interdisciplinary Department of Supportive Care in Oncology), Centre Léon Bérard in Lyon. Even though this is an observational study, its key strength is that data were collected prospectively, rather than retrospectively. Among its weaknesses is the size (it only examined 50 patients) and, from my perspective, this part of the rationale (IO=integrative oncology; CTh=Complementary and Alternative Medicine):
Currently, enthusiasm for IO is growing among patients and emergent framing needs and guidance increasingly recognized among medical professionals [5]. IO services at the National Cancer Institute (NCI)–designated comprehensive cancer centers have increased from about 50% in 2009 to 80% in 2016 [6]. American academic cancer centers (Memorial Sloan Kettering Cancer Center, MD Anderson Cancer Center, etc.) have ongoing training programs including resources about integrative medicine [7]. In France, an increased number of initiatives are underway to improve IO implementation within conventional care structures [8] or in the associative field. In France, the University College of Integrative and Complementary Medicine (CUMIC) was created in 2017, and following the example of the Society for Integrative Oncology (SIO) founded in 2003, the French Society of Integrative Oncology (SFOI) was recently established in 2023 by oncologists and/or experts in integrative care.
However, the lack of scientific evidence is prejudicial and many healthcare professionals (physicians and healthcare teams) prefer to avoid discussion related to CTh [9], and referral to dedicated consultations or professional experts is still rare. Patients are also reluctant to spontaneously express their use of CTh with their oncologist [10]. The use of these therapies is therefore mainly decided on an isolated, individual basis. IO consultations have progressively emerged in France and worldwide, to overcome these difficulties, allow patient to express their needs, improve referral and individualized care pathway. IO consultations allow to better inform patients on CTh, CTh-associated risks and beyond the opportunity for better patient/physician relationship would contribute to improve patients’ quality of life.
“The lack of scienitific evidence” for IO is “prejudicial”? They write that as though it were a bad thing! You don’t like the “prejudice” against “complementary and alternative medicine” (which we in the English-speaking world abbreviate as “CAM”)? Then produce some evidence that what you are doing is safe and effective. Basically, as is the case with most of these sorts of studies, this is more of a marketing exercise, specifically an analysis of the market, to identify ways to sell more product. That doesn’t mean that it doesn’t provide some useful insights, though.
The study producing the data is THERAC, which stands for “THERApies Complémentaires (Complementary Therapies):
The prospective, monocentric, exploratory, observational, descriptive study THERAC included all consecutive adult patients, treated at the Leon Berard Comprehensive Cancer Center (CLB) (Lyon, France), able to understand, read, and write in French, attending an IO consultation. The descriptive nature of the study was not supported by a priori hypotheses; the number of participants was set at 50 consecutive patients eligible to IO consultation in the next 6 to 12 months. All patients received dedicated information and provided informed consent. THERAC falls under the French regulation known as “Méthodologie de Référence MR-004.” This methodology was established by the French data protection authority (CNIL) to provide a legal framework for processing personal health data without requiring explicit patient consent, as long as certain strict conditions are met (here: data analysis projects where no active intervention or modification of patient care occurs). The institution (Leon Berard Cancer Center) certified that the study complied with the M004 rules. We ensure that Human Ethics and Consent to Participate declarations are available.
Basically, THERAC is a database of patients seeking integrative oncology services at the Léon Bérard Comprehensive Cancer Center in Lyon. The researchers used clinician-rated assessments at three fixed time points: First, at the moment of inclusion in the study; second, three months later; and, finally, six months later. The idea was to capture the consultation process as it unfolds in routine clinical practice and obviate the possibility of poor memory and recall bias on the part of the subjects coloring their recollections. Subjects were recruited consecutively, until the target accrual of 50 patients was reached. This, of course, is one of the weaknesses of the study; it only examines the experiences of 50 patients, and it took nearly a year (November 2021 to January 2023) to recruit them. As reported in the Results, the patients recruited were predominantly women (n = 45, 90%), with a median age of 52 (26–76) years, and a high socioeconomic status (Table 1). The latter characteristic is not surprising to me, given how much “integrative” medicine is targeted towards people with wealth. I was also not surprised that the cohort was predominantly made up of women, but I was surprised at how lopsided the distribution was. I would have predicted 60-70% women, not 90%. Given this distribution, it is not particularly surprising that more than half the patients (56%) were breast cancer patients. Moreover, most patients came from urban areas (80%), including 44% from wealthy metropolitan areas represengint only 22% of the French population, with only 36% coming from what the authors describe as “precarious” population districts.
In other words, the population studied was not representative of the French population in general, but, again, that is not surprising given how much of the “integrative medicine” marketed by “respectable” academic medical centers pulls in the affluent. In fact, it’s easier just to show you a bar graph of the percentages of patients expressing specific expectations:
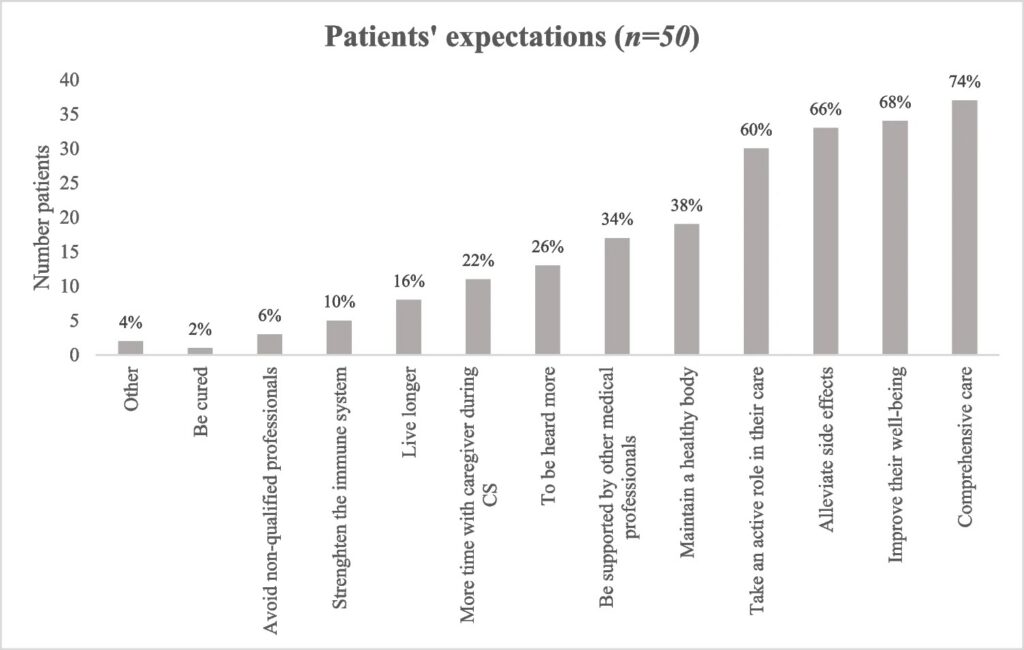
These results should not be particularly surprising, as they do tend to align with previous data examining motivations of patients seeking “integrative” oncology care. Most such patients do tend to mistakenly conflate “holistic” care with “integrative” care. It is therefore not particularly surprising that, according to the investigators that patients “with follow-up completed were globally very satisfied with the IO consultation at 3 months (n = 27/29, 93%) and at 6 months (n = 11/11, 100%).” Interestingly, time spent with caregiver was a relatively minor expectation, which tends to conflict with the narrative that what “integrative” medicine patients seek are doctors and other caregivers who will spend more time with them.
I said that I was “less interested” in what was actually prescribed in the study, but that doesn’t mean that I was not interested at all. So here’s a graph showing what patients were offered:
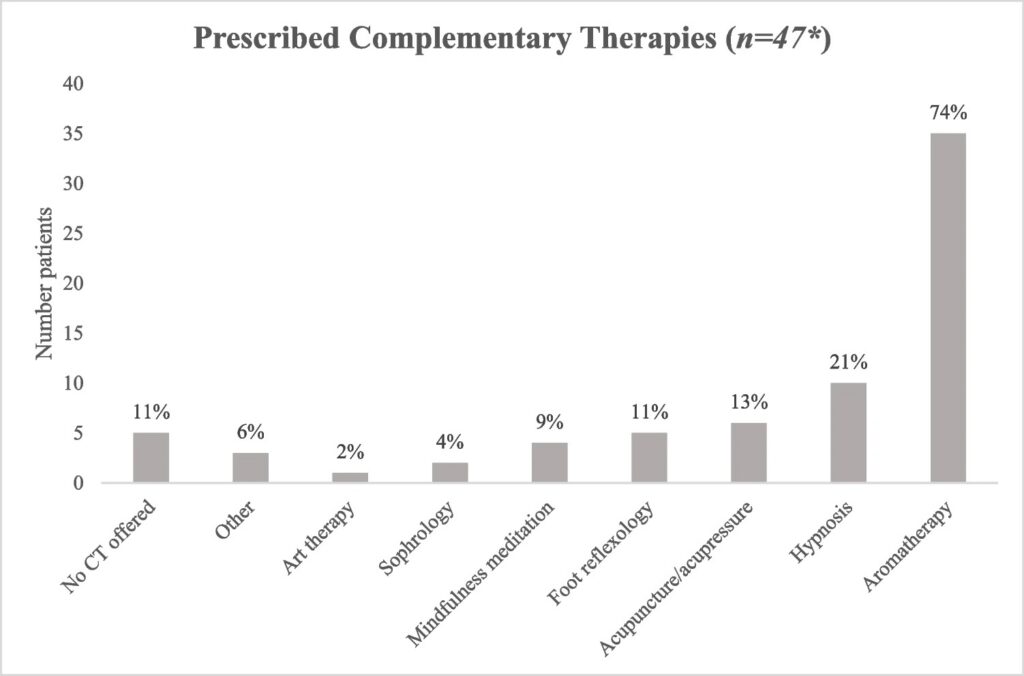
I must admit that I was surprised at how much aromatherapy was offered and how little acupuncture and mindfulness were offered. However, if I knew more about the cancer center where this study was carried out, it wouldn’t have surprised me:
Aromatherapy is easily available within the Centre Léon Bérard through established protocols in both inpatient and outpatient settings, supported by the development of a dedicated clinical aromatherapy service in 2017 [26]. The relatively low cost and simplicity of administration of essential oils may also explain the widespread use of aromatherapy. The main indication in our study was anxiety management and sleep management, in consistence with current international IO recommendations [27].
In other words, aromatherapy and essential oils ruled this study because aromatherapy was the most easily offered CAM therapy at the cancer center where the study was being done. Convenient that. Of course, as I like to say, acupuncture is nothing more than a theatrical placebo, while reflexology is nothing more than a foot massage with delusions of grandeur. I was unfamiliar with sophrology, but it appears to be nothing more than a different form of meditation and mindfulness that is described as as “dynamic relaxation” method inspired by phenomenology, hypnosis, yoga, Tibetan Buddhist meditation, Japanese Zen meditation, progressive muscle relaxation, autogenic relaxation training, psychology, neurology.
Near the end of the Results and in the Discussion section, the authors give away the real game; i.e., the real purpose of the study:
Patients often resort to CTh on their own, without informing medical professionals, which isolates disciplines [32]. A collaborative organization involving different CTh professionals would instigate a synergy probably more relevant than strict superpositions of individual therapies [33] and would contribute to the development of an identified integrative care network at a national scale. Nurse coordinators and oncologists particularly concerned with CTh risks should be able to appraise patient understanding and feelings, and to detail CTh-related constraints and limitations, and appropriately refer patients to IO consultation. Medical professionals need to build confidence to convince patients to adequately protect themselves, through providing improved information regarding CTh-related potential risks. Lastly, medical professionals feared “patient unrealistic expectations” and patient perception of “hoping to get cured,” as previously reported [3], suggesting they may be challenged in addressing IO psychological impact.
And, finally:
IO consultations implementation in our French comprehensive cancer center constitutes an innovative approach which need to be further develop to better address patients’ needs and expectations, and contribute to patient healthcare satisfaction. Such initiatives need to be developed and encouraged to promote an advanced comprehensive care of cancer patients in a reassuring relational context.
My retort to this is the same retort that I always make whenever faced with the justification that quackery like acupuncture, reflexology, etc. needs to be “integrated” into cancer care: You don’t need to “integrate” quackery with medicine to “better address patients’ needs and expectations, and contribute to patient healthcare satisfaction.” Nor do you need to integrate quackery to provide true “holistic care.” While it is true that in the US, our primarily for-profit healthcare system puts time and resource constraints on practitioners that make it very difficult to address the “whole patient” in many cases, the answer to that is not to throw quackery into the gap between what patients want and what the healthcare system can achieve.
But what about Asia?
Now, on to Taiwan…
The next study to be considered here was published a couple of weeks ago in BMC Complementary Medicine and Therapies. Entitled Intentions, effects, and challenges associated with the use of traditional Chinese medicine for breast cancer: a qualitative study from TCM physicians, it looks at, unfortunately, physicians who use traditional Chinese medicine to treat cancer patients. Touted in what appears to be a press release as a “rare insider view of this dual-track care model, drawing on in-depth interviews with experienced TCM physicians who treat these patients every day,” this study examines the issue primarily from the perspective of TCM practitioners who are physicians, in particular the “challenges” of combining TCM with “Western medicine” (abbreviated, annoyingly, in this article as “WM”), as if such a combination is even desirable.
The design of the survey is described thusly:
To be eligible for participation in this study, TCM physicians were required to be currently assuming the position of an attending physician and to have treated patients with breast cancer–related conditions within the previous year. Purposive sampling interviews were conducted with TCM physicians from a municipal public hospital in northern Taiwan, who comprise the “TCM Cancer Special Clinic” and “Enhanced Daycare of TCM for Cancer Treatment.” Physicians who met the research criteria were included in this study and scheduled for in-depth interviews. During the initial recruitment phase, attending physicians with sufficient clinical experience were purposively approached. Subsequently, snowball sampling, base on the participants’ referrals, was conducted to explore the perspectives of TCM physicians across hospitals. Data collection was discontinued once saturation was reached; specifically, the recruitment of additional participants via snowball sampling ceased when no new factors emerged from the data. All interviewees provided written informed consent before their interviews.
Participants were asked the following questions (BCP=breast cancer patients):
Interview recordings were transcribed verbatim for further analysis. The interview guide comprised the following questions:
- What is your experience with cancer treatment?
- What do you think are the reasons for BCPs using TCM?
- How do you think the stage of breast cancer affects the use of TCM by BCPs?
- How effective is TCM in treating breast cancer?
- If the patient is simultaneously seeking WM, how would you discuss TCM use or recommendations with the patient?
- Do you think there are any limitations in the current use of TCM in breast cancer care? Do you have any suggestions for improvement?
Question #4 should be easy to answer: TCM is not effective at treating breast cancer. Question #5 should also be easy: Use conventional science-based medicine to treat your cancer. I tend not to recommend TCM to treat breast cancer, but if you insist make sure that whatever TCM you choose doesn’t interfere with your treatment. My snarky answer to the last question would be: There aren’t nearly enough limitations in the current use of TCM to treat breast cancer. But that’s just me, and I’m not a TCM practitioner…obviously.
Indeed, as I like to say, TCM is a system of medicine based on a prescientific understanding of how the human body functions and becomes ill that has a lot in common with “Western” or European humoral theory, in which imbalances between the four “humors” (blood, yellow bile, black bile, and phlegm) determine health and disease. In TCM, this article actually lays it out. See the similarities:
In TCM, body constitution is interpreted as a reflection of individual health status, determined by differentiating the Yin-Yang balance of the five fundamental substances (essence, Qi, blood, body fluids, and spirit) as well as the five viscera (heart, liver, spleen, lung, and kidney). Because TCM considers disease to be caused by a Yin-Yang imbalance, such deviations in body constitution can influence a patient’s overall health and may affect the survival rate of cancer patients [26–28].
Whenever I see this description of TCM, I can’t help but add this little image:

What was interesting about this study is that the TCM practitioners identified distress as a key motivator for women with breast cancer to seek TCM. The press release notes that in Taiwan’s health system, TCM is licensed, insured, and provided in dedicated hospitals and clinics, which means that patient’s don’t have to choose between science-based medicine and TCM, which is why many use both. The main finding of the study, though, is described thusly:
To the best of our knowledge, this is the first study to comprehensively explore the intentions, effects, and challenges associated with the use of TCM by BCPs from the perspective of TCM physicians. Our findings indicated that many BCPs tended to seek TCM care primarily to relieve the side effects of conventional treatment. According to TCM physicians, TCM care improves the body constitution of BCPs, potentially enabling the management of their tumors. However, certain challenges remain in TCM care. For example, some TCM physicians mentioned that TCM often encountered rejection from WM physicians. Nonetheless, the TCM physicians acknowledged that WM remains the primary treatment for breast cancer. They believed that TCM and WM can complement each other to improve health outcomes for BCPs. Medication use, health insurance, and policy restrictions of TCM emerged as key challenges in current breast cancer care.
Oh, dear. Some “WM physicians” reject TCM? What a shame. It should be nearly all. The claim that TCM care “improves the body constitution” of breast cancer patients is also mainly the perception of TCM practitioners, not anything for which any concrete evidence is presented. During the discussion, the authors state:
Depending on their culture and personal experiences, patients with cancer often consider TCM for their healthcare needs [21]. We previously reported that after receiving their diagnoses, BCPs often seek means to alleviate the side effects of conventional treatment, which becomes their primary intention for seeking TCM [15]. Similarly, a systematic review revealed that patients with cancer in Taiwan often seek TCM to address what WM cannot achieve—for example, eliminating the root of the disease [22]. These patients seek to improve their body constitution and well-being through TCM. Health insurance may influence how patients with cancer use TCM [22]. In the present study, some TCM physicians indicated that TCM care can address the limitations of conventional treatment and stabilize the condition of BCPs. The physicians also highlighted that combining WM with TCM can improve health-related outcomes and quality of life.
Again, nothing in this study actually supports the claim that combining “Western medicine” and TCM can “improve health-related outcomes and quality of life. The authors do cite a number of questionable studies suggesting that this is the case, as well as some systematic reviews that suggest that certain herbal medications have anti tumor activity. This is, of course, nothing more than pharmacognosy, the branch of pharmacology that studies medicinal substances that can be isolated from plants and other natural products. You don’t need the rest of TCM to use pharmacognosy to improve the care of cancer patients, given that a large number of current cancer chemotherapeutics are either derived from natural products or are chemically altered components of natural products designed to give the medicine more desirable properties.
None of that stops the authors from arguing:
The present study revealed a gap between WM and TCM. Some TCM physicians mentioned that TCM and WM may be complementary. They highlighted the use of WM as the subjective treatment and TCM as an adjunct therapy as the best approach for breast cancer treatment. Therefore, further WM–TCM collaboration and additional evidence-based research into TCM are required to avoid potential health impairments and conflicts in the healthcare system [40, 47] and improve the health outcomes and quality of life of patients with cancer [48, 49]. A study reported that after completing a semester involving a TCM-based medicine curriculum, WM students could develop a better understanding of TCM and viewed TCM knowledge as beneficial to WM practice [50].
Sure. Indoctrination can work.
The bottom line from these two studies is that “integrative” oncology, whether it’s of the sort practiced in France based on its region-specific collection of unproven and pseudoscientific treatments to be added to conventional oncology or of the Chinese and Taiwanese variety, in which TCM is the collection of unproven and pseudoscientific treatments to be added to conventional oncology, does not really add anything desirable to conventional therapy that couldn’t be added by simply providing more resources and time to cancer doctors. It does, however, show that, whether in Europe or Asia, there are still large numbers of people who misperceive the addition of unproven and disproven therapies based on prescientific conceptions of how the body works to be a desirable thing.
Now here’s the problem. Both of these studies come from academic medical centers, where the more harmful aspects of “integrating” quackery with science-based medicine are usually under control. (Usually.) What happens when patients seek “integrative” care out in the wild? For that, we have oncologist Dr. Alex Morozov’s report at ETP News, entitled Selling Hope Chapter I: Going Undercover. (Full disclosure: I have been asked to be on the board of directors of ETP News and will likely soon be officially on the board.)
What is the reality? Probably more like Alex Morozov’s experience
We already established a couple of weeks ago that there are many “integrative” cancer clinics and medical centers, both in the US and, in particular, in countries like Mexico, where regulation of medicine is—shall we say?—somewhat more lax. We also discussed how a recent NYT interview with Trisha Thadani, whose father was the subject of the NYT article on the quackery of “integrative oncology” clinics, bad actors entice desperate cancer patients. Here, Thadani was asked a question on this:
He couldn’t get a clear prognosis from his oncologist because every patient is different. That propelled him on a search for alternatives. What did he find?
My dad was inundated with ads for alternative cancer treatment clinics around the country and in Mexico. Clinics pay to target people who search for terms like “Stage 4 cancer survival rate” and “chemotherapy side effects.” He spoke to several other clinics — some of which I would later learn have troubled records — before picking one in Arizona.
What “reputable” integrative oncology clinics at academic medical centers (which are bad enough, given how their universities and reputations give quackery the appearance of legitimacy) frequently forget is that they are in competition with institutions whose dedication to evidence and science-based medicine is far below theirs, which leads patients to clinics like the one described in the NYT article, Envita. That last pitch is particularly bad, because, as the two studies I discussed above show, patients often seek “integrative” care because they are most concerned about the side effects of chemotherapy, radiation, surgery, and other therapies used to treat cancer.
This brings us to Dr. Morozov’s odyssey. The entire article is worth reading in full (as, I presume, subsequent parts of the story will be). In brief, Dr. Morozov posed as a stage IV colorectal cancer patient:
To see first-hand how and why these supplements are prescribed to patients, I went undercover, posing as a cancer patient myself. I prepared a fake colonoscopy report showing that I was diagnosed with colon cancer, a CT scan report showing liver metastases, and an imaginary oncologist’s note recommending chemotherapy.
I then saw a series of clinicians. I did not tell them that I am a physician myself. If they asked what I did for a living, I told them that I have an interest in AI and computers, which is true. My goal was to make sure that my experience would be similar to that of most patients, without any kind of special treatment.
Dr. Morozov also noted:
Undercover journalism has a long history, going back to pre-Civil-War America, when Northern reporters attended slave auctions in the South, posing as prospective buyers. Today’s Code of Ethics of the Society of Professional Journalists, of which I am a member, advises reporters to “avoid undercover or other surreptitious methods of gathering information unless traditional, open methods will not yield information vital to the public.” In my case, these conditions were clearly met. Even if I were to find cancer patients willing to tell me about their experiences, I would not be able to piece together their full stories from their recollections alone.
Fair enough. I buy this rationale. Certainly, I could never have pulled this off. I’m too bad an actor and my poker face is not very convincing most of the time.
Again, I urge you to read the whole thing. Let’s just say that Dr. Morozov’s experiences were not unlike what I would have expected. He was offered a whole lot of expensive “functional medicine”-like blood tests, supplements, and other treatments, all at very high cost. Most incredible to me were the costs of his consultations. First, though, here’s how Dr. Morozov describes the beginning of his odyssey:
My first stop was Lubbock, Texas, to see Dr Ben Edwards. His company, Veritas Wellness, “started as a small functional medicine clinic and has now evolved into a worldwide online wellness and education platform,” according to a local business organization. Veritas sells its own line of branded supplements, which means that the bottle says “Veritas Wellness” on the label.
Edwards referred me to a former colleague, also in Texas, who follows a “metabolic approach to cancer”. I then went for a second, third, fourth and fifth opinion at other providers, always bringing my growing pile of prior records and recommendations. I saw a naturopathic doctor (ND) who serves as Clinical Professor at a major academic medical center; a senior board-certified medical oncologist at the same center; a functional medicine physician at another major academic center; a registered dietician at the same center; a board-certified medical oncologist at a third major academic center; and an AI bot on a wellness platform. More on each visit in the following chapters.
Ben Edwards has been featured on this blog before. He’s a profoundly antivax doc whose name has appeared for his use of quackery to treat measles patients during the West Texas measles outbreaks last year. His clinic, Veritas Wellness, appears to work primarily on a subscription model to provide ongoing services, starting at $29 a month (plus costs for labs and supplements, of course, as well as whatever video courses and books you might want to order). To give you an idea of how far down the rabbit hole of woo Edwards lures his marks, just note that he apparently believes in Masura Emoto’s “magic water” that takes on the “intentions” directed at it, as well as Jacques Benveniste’s bogus experiments. Let’s just say that it all looks like homeopathy, without Edwards ever actually using the word homeopathy in his blog post about it, kind of like this post appears to be advocating the quackery known as live blood cell analysis without actually using the term. To give you an idea of his approach to evidence, I’m just going to drop a link to his blog post Theory vs. Truth. Wow. It’s like the creationist “just a theory” mischaracterization of evolution applied to all of medicine. Dr. Morozov further elaborates on Dr. Edwards journey from reputable family medicine doctor moving to an underserved part of Texas in 2009 to his current status as, in my not-so-humble opinion, an integrative quack and, now, cancer quack.
Just look at the email Dr. Edwards sent Dr. Morozov after his intake information was recorded:
I believe you are making a very wise decision to look into some complementary and alternative modalities for overcoming cancer. Here is exactly what I tell my patients who get a diagnosis of cancer…
Proceed with your oncologist to get the official diagnosis… Conventional medical techniques typically do really good with stage 1 (just cut it out basically). But, once it has spread at all, then in general the rates of survival with conventional techniques start to go down pretty fast. This is when I really, really encourage looking at adding in complementary and alternative things. SOMETIMES the conventional protocols do pretty good with SOME cancers that are stage 2, 3 and 4, but for the most part the more advanced stages/spread are not “curable”, and the conventional protocols just “extend life a little”… Consider asking some alternative clinics if they have data on their 5 year survival rates for your particular cancer.
Nice of him to admit that a lowly breast cancer surgeon like myself can actually help cancer patients, but only if they are stage I. In any event, this is standard cancer quack boilerplate about how “conventional oncology” can only treat local cancer but you need them and their magic to treat anything more advanced.
The other thing that depressed me about that passage was that Dr. Morozov was referred to two oncologists, a functional medicine quack, and a naturopath, all spread out over three academic medical centers. I can sort of guess which centers these might have been, although they are not mentioned…yet. Perhaps my assessment that academic medical centers, especially university-affiliated centers, try to guard their reputation for being science-based. In any event, the fact that these practitioners. I tried to guess which clinic was offering a “metabolic approach to cancer,” but using Google search, Gemini, and Claude, I discovered that there are just too many such clinics in Texas for me to hazard a strong guess, which depressed me even further.
Fortunately, Dr. Morozov had an excellent retort to his email:
Second, “asking” a for-profit “alternative cancer clinic” for their survival rates? From a consumer perspective, my advice to cancer patients would be the opposite: be very skeptical of outcome data self-reported by a for-profit cancer clinic. They are biased. They have a conflict of interest. They want your business. Look at each treatment individually and find studies done by independent researchers.
Third, trustworthiness aside, such numbers are hard to find. I searched and searched, but could not find an alternative cancer clinic with independently audited, cancer- and stage-specific five-year survival data demonstrating better outcomes than appropriately matched standard oncology care.
Indeed, a much less dodgy—but still dodgy—chain of “integrative” cancer centers, formerly known as the Cancer Treatment Centers of America, used to routinely exaggerate its survival statistics. The point is, you will never find accurate, reliable outcomes data from clinics like Envita or Veritas. If you do find such statistics, it’s advertising, not science.
In any case, as Dr. Morozov went to different practitioners recommended first by Edwards and then by subsequent practitioners whom he saw, this happened:
Over the course of my consultations, I was ordered 109 different blood tests (not counting repeats). Many tests had multiple measurements. For example, the complete blood count is one test that measures white cells, red cells, etc. My tests included a total of 230 different measurements.
I was charged enormous fees. Many were not covered by insurance at all. A two-hour zoom consultation cost me $3000. Supplements, about $1000/month. Blood, urine, stool and saliva tests, over $3000. Other visits could be covered by insurance, but I paid out of pocket. For a 7-minute discussion with an oncologist I was charged $1800. A one-hour consultation with a functional medicine doctor cost me $1400. I was simply informed of these prices and expected to pay. I was never asked about my financial situation or offered any financial assistance.
One provider was apologetic about the cost of supplements. He emphasized free shipping and discounts where possible. He made it sound like his recommendations were optional (“only if affordable,” he wrote in his clinical note). In my opinion, that’s not a good strategy when you are wearing a white coat and speaking with authority to a cancer patient. If the benefit is questionable, don’t ask the patient to spend the money. And if the benefit is clear, help them pay.
Indeed. And what can one do that’s worth $1,400 an hour—or, as was the case with the oncologist, over $15,000 per hour if seven minutes cost $1,800. As I like to say about these quacks, nice work if you can get it. Unfortunately, my sense of ethics would never allow me to go down this path.
Again, I encourage you to read Dr. Morozov’s Substack post in full. The main reason that I wrote this post is to emphasize how there is a massive disconnect between what “integrative” oncology practitioners in academic medical centers think that integrative medicine is and involves and what “integrative” oncology actually does involve on the ground level, where patients are brought in. Academic “integrative” oncology practitioners view their craft as somehow being the “best of both worlds,” in which alternative medicine is added to complement science-based oncology and relieve symptoms. The reality is far closer to what Dr. Morozov and Trisha Thadani have reported.